B Berthe, S Doumbia, H Samake, S Tall, N Sylla, D Goita, SO Traore, OM Traore, I Teguete, I Konate, Y Traore
22-Jan-2026
Introduction : All pregnant women are at risk of experiencing obstetric complications, which more often than not necessitate blood transfusions. Hemorrhages occurring during pregnancy, childbirth, and the postpartum period are the leading cause of maternal death worldwide. The objective of this study was to evaluate the role of blood transfusion in the management of obstetric emergencies in the health districts of Bamako, Koulikoro, and Ségou. Methodology: This was a multicenter, cross-sectional, descriptive, and analytical prospective study conducted from January 1, 2017, to December 31, 2019. We performed exhaustive sampling of all blood transfusion cases during the pregnancy and postpartum period, regardless of the outcome. The data were analyzed using SPSS software (version 20). Results: We collected 647 cases of blood transfusions out of a total of 3,971 obstetric emergencies, representing a prevalence of 16.30%. The average age was 28 years. Our sample consisted primarily of uneducated, multiparous women who were housewives, domestic workers, or engaged in unpaid work and were being evacuated. Obstetric hemorrhages and iron deficiency anemia were the indications for transfusion in 74.23% and 17% of cases, respectively. In one-third of cases, the blood demand was not fully met (30%). Eighteen (18) cases, or 2.8%, of maternal deaths were recorded. Conclusion: The continuous availability of blood products improves maternal prognosis.
Transfusion, Emergency, Obstetrics
Introduction : Toute femme enceinte est exposée au risque de complications obstétricales, nécessitant souvent des transfusions sanguines. Les hémorragies survenant pendant la grossesse, l’accouchement et la période post-partum constituent la première cause de mortalité maternelle dans le monde. L’objectif de cette étude était d’évaluer le rôle de la transfusion sanguine dans la prise en charge des urgences obstétricales dans les districts sanitaires de Bamako, Koulikoro et Ségou.
Méthodologie : Il s’agissait d’une étude prospective multicentrique, transversale, descriptive et analytique, menée du 1er janvier 2017 au 31 décembre 2019. Nous avons effectué un échantillonnage exhaustif de tous les cas de transfusion sanguine survenant pendant la grossesse et la période post-partum, quel que soit l’issue. Les données ont été analysées à l’aide du logiciel SPSS (version 20).
Résultats : Nous avons recensé 647 cas de transfusions sanguines sur un total de 3 971 urgences obstétricales, soit une prévalence de 16,30 %. L’âge moyen était de 28 ans. Notre échantillon était principalement constitué de femmes sans instruction, multipares, sans emploi rémunéré ou travaillant dans le secteur domestique, et évacuées. Les hémorragies obstétricales et l’anémie ferriprive constituaient les indications de transfusion dans respectivement 74,23 % et 17 % des cas. Dans un tiers des cas, la demande en sang n’était pas entièrement satisfaite (30%). Dixhuit (18) cas de décès maternels, soit 2,8 %, ont été enregistrés.
Conclusion : La disponibilité continue des produits sanguins améliore le pronostic maternel.
Mots-clés : transfusion, urgence, obstétrique.
On October 16, 1914, the first direct blood transfusion of the First World War took place at the Biarritz Hospital: Isidore Colas, a Breton recovering from a leg wound, saved Corporal Henri Legrain of the 45th Infantry Regiment, who had arrived from the front exsanguinated, by donating his blood. Their blood must have been compatible, since the operation was successful. By the end of 1914, forty-four (44) transfusions had been performed in France using this method, with promising results, despite the complete lack of knowledge about blood groups (Association of Voluntary Blood Donors of the Canton of Lillebonne, 2010) [1].
Blood transfusion (BT) is the transfer of blood or blood components from one individual (donor) to another (recipient) [2]. The obstetric setting predisposes to blood transfusion (BT) due to the frequency of hemorrhages and associated pathologies, which remain a significant cause of maternal morbidity and mortality in both developed and developing countries [3,4,5]. The main indications are: hemorrhages, especially postpartum [6], anemia due to iron, folate, and vitamin B12 deficiency, and malaria [7]. Transfusion allows obstetric and resuscitation care to be adapted to the close monitoring of vital functions, bleeding rate, and hemostasis. This transfusion is essential not only to replace blood loss and maintain tissue oxygenation, but also to correct dilutional and/or consumption coagulopathy, which frequently complicate obstetric hemorrhage [8]. Thus, maternal prognosis sometimes depends on the timely availability of adequate labile blood products (LBP) [9,10]. We initiated this work to study the use of labile blood products in obstetric care in Mali. The objective of this study was to evaluate the use of labile blood products in obstetric care.
Data were collected prospectively from January 1 , 2017, to December 31, 2019. Data collection covered three health districts in Mali, selected based on staff availability for data collection. The health districts involved were Commune V (Bamako), Fana (Koulikoro), and San (Ségou). We studied the profile of transfused patients, their medical history, indications for transfusion, Rh factor, availability of blood products, blood products used, transfusion-related complications, and maternal prognosis. We performed exhaustive recording of all transfusion cases during the pregnancy and postpartum period, regardless of maternal outcome during the data collection period. The data were analyzed using SPSS software (version 20). The odds ratio (OR) was calculated and presented with its limits in the 95% confidence interval (95% CI), and the significance level was set at p<0.05. The analyses were performed using Epi Info 7.2 software. For ethical considerations, confidentiality was respected by assigning anonymity numbers to all records.
We collected 647 cases of obstetric emergencies that received a blood transfusion out of a total of 3,971 obstetric emergencies, representing 16.30%. The average age of the patients was 28 years, with a range from 15 to 49 years. More than two-thirds of the patients (68.62%) were between 20 and 34 years old. Among our patients, 85.78% were unemployed; 46.67% had four or more children; 11.90% were single; and 88.40% had no formal education. 88.10% were married. Housewives/domestic workers accounted for 81.3% of the cases.
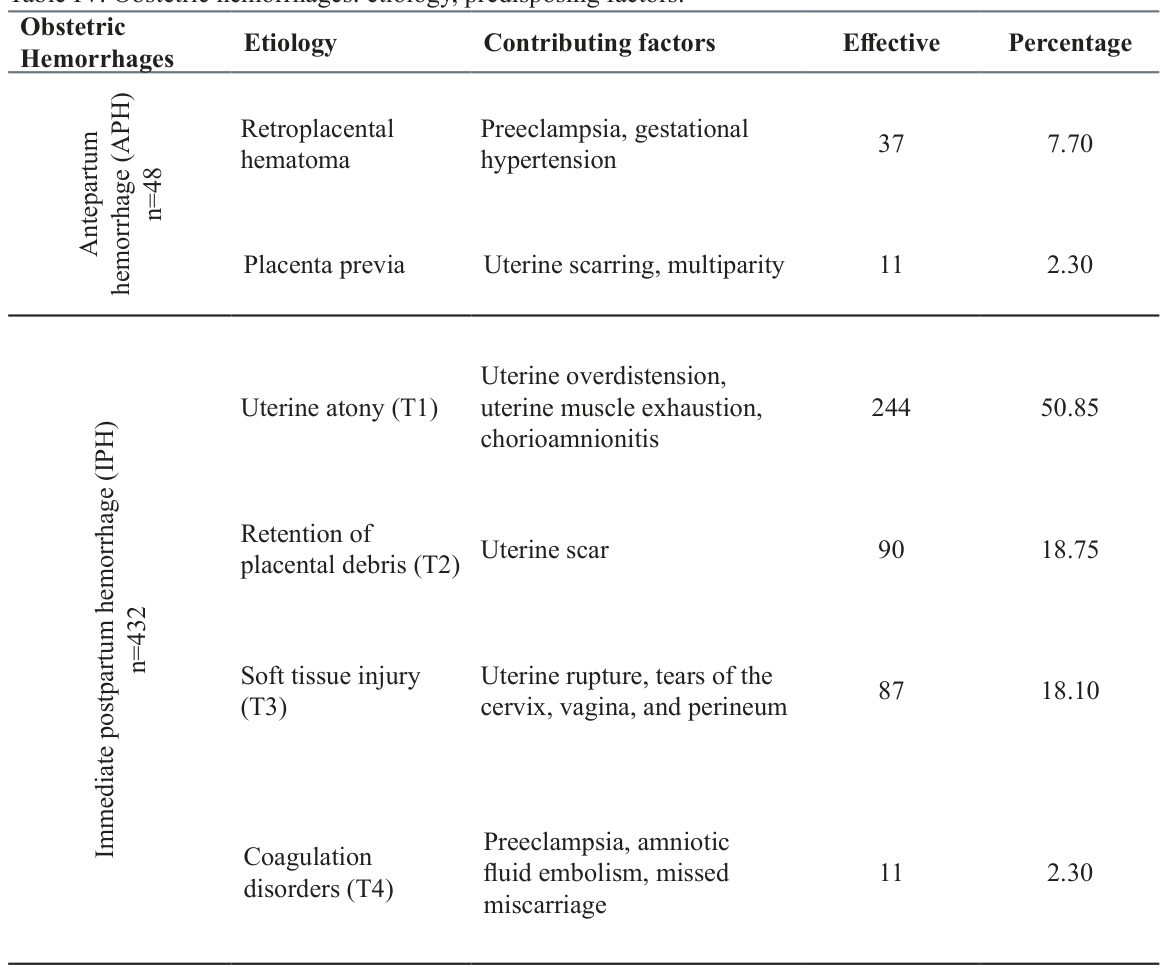
Fourteen patients had a history of transfusion, five had major sickle cell disease, and two were HIVinfected. Multiparous women represented 46.67% of the patients, compared to 35.4% who were primiparous. Referrals for medical evacuations accounted for 60.74% of cases. Obstetric hemorrhage was the reason for admission in 376 cases (58.10%), of which 273 (72.60%) were immediate postpartum hemorrhages. Other reasons for admission included dizziness in 78 cases (12.05%), exertional dyspnea in 71 cases (10.97%), or a combination of both in 122 cases (18.88%). Decompensated anemia was present in 336 cases (51.60%).
The hemoglobin level on admission was ≤ 6 g/dL in 477 cases (73.73%). It was between 7 and 8 g/ dL in 129 cases (19.93%) and between 9 and 10 g/ dL in 41 cases (6.34%). Blood groups O+, B+, A+, and AB+ were present in 47.30%, 25.34%, 18.23%, and 4.80% of cases, respectively. Rh blood groups O-, A-, B-, and AB- were present in 1.54%, 1.23%, 0.92%, and 0.64% of cases, respectively. The main indication for transfusion was obstetric hemorrhage (74.23%), of which 60.40% was postpartum. These hemorrhages were associated with comorbidities such as iron-deficiency anemia in 17%; malaria in 4.60%; and major hemoglobinopathies in 4.17%. In one-third of cases, the blood request was not met (30%). Thus, two units of blood were requested in 73.40% of cases, while 37.86% were fully delivered (OR = 1.76; CI [1.35–2.31]). The hemoglobin level ≤ 6 g/dL decreased from 73.73% to 64.45% before and after transfusion, a statistically significant difference (p = 0.000; OR = 1.62; CI [1.27–2.07]). Whole blood represented 99.22% of the blood products transfused. Transfusion-related adverse events included acute pulmonary edema in 5 cases, anaphylactic shock in 4 cases, hyperthermia-chill syndrome in 3 cases, urticaria in 3 cases, and lumbar pain in 2 cases. Eighteen (18), or 2.8%, patients died.
Table I : Epidemiological and clinical aspects of transfused obstetric emergencies
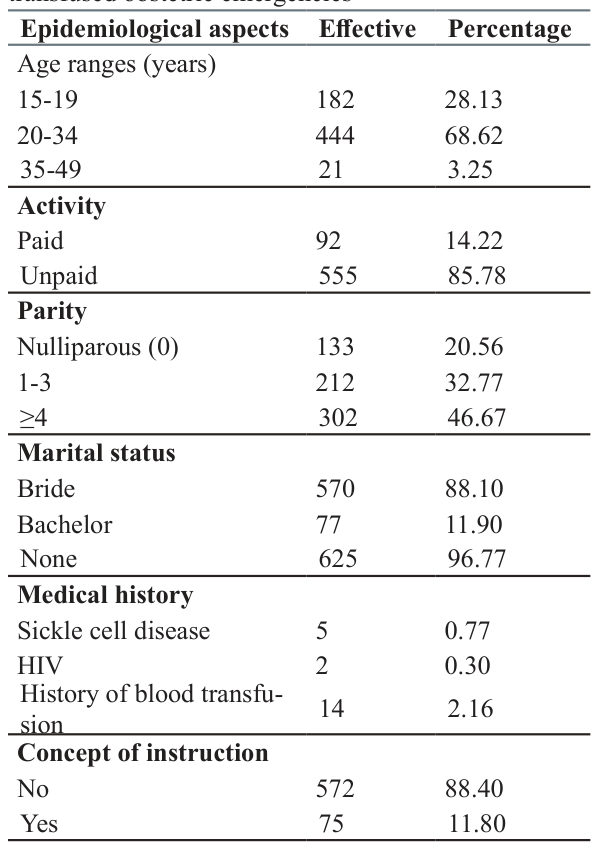
Table II: Biological aspects of transfused obstetric emergencies 2017-2019 , CHU Gabriel TOURE, Bamako, Mali.
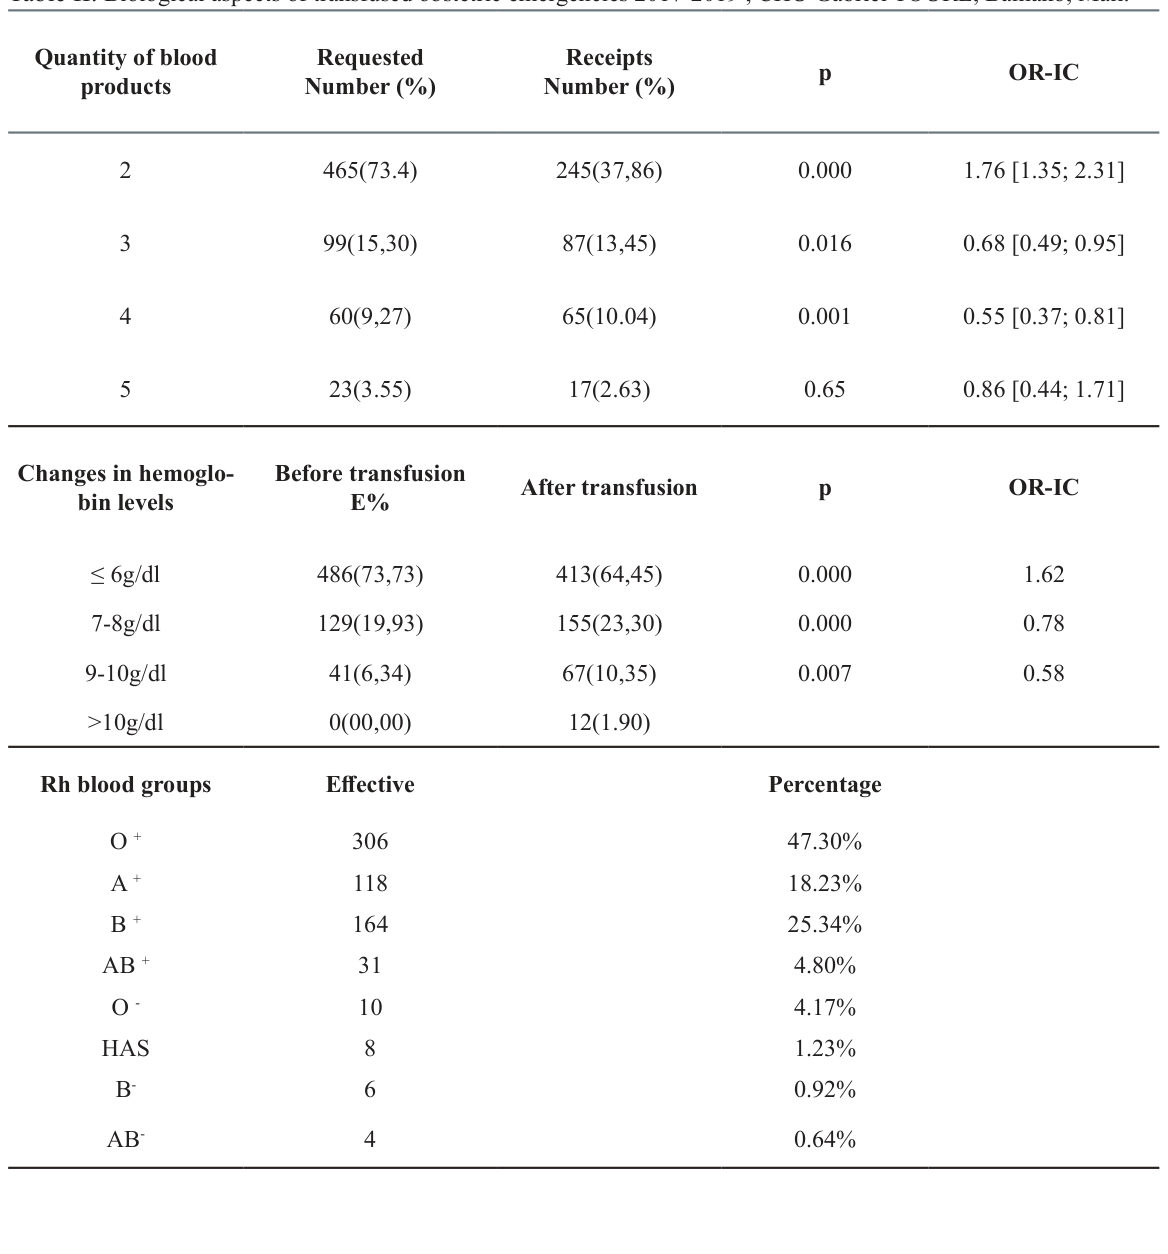
Table III: Indications for blood transfusion in obstetric emergencies
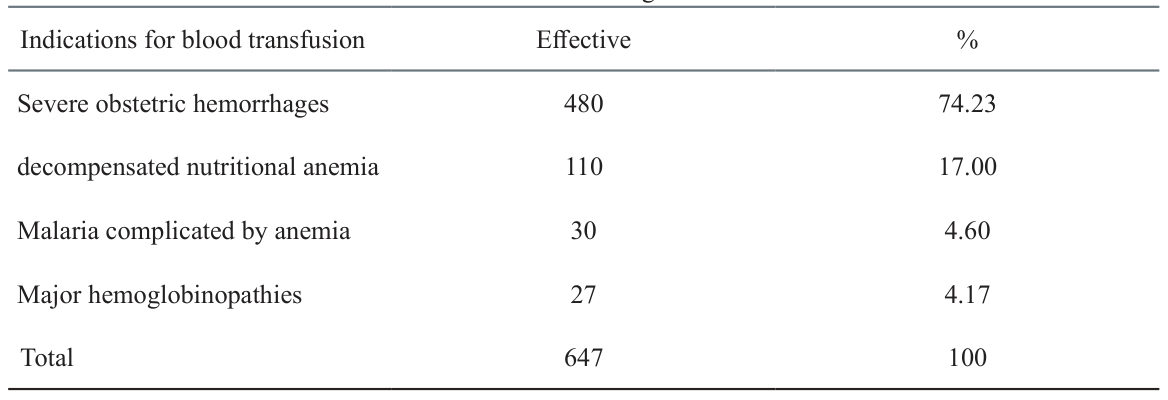
Table IV: Obstetric hemorrhages: etiology, predisposing factors.
In our study, the blood transfusion rate was 16.30%, which is higher than that reported by Louati et al. [11] and Ben Ayed et al. [12], who reported rates of 0.82% and 0.76%, respectively. Our high rate could be explained by undernourishment in the population, the absence of or inadequate prenatal care depriving many patients of iron and folic acid supplementation, or by significant shortcomings in the early preventive and curative management of postpartum hemorrhage. The average age of the patients in our study was 28 years, with a range of 15 to 49 years. Louati et al. [11] in Tunisia found an average age of 31.5 years. Our sample consisted of 11.90% single women, 88.1% uneducated women, and 81.3% homemakers and domestic workers. Patients were discharged in 60.74% of cases. Multiparous women represented 46.67%. In 47.30% of cases, patients had not received prenatal care. This uniquely complex profile makes patients particularly vulnerable to anemia and immediate postpartum hemorrhage (IPH). Obstetric hemorrhages were the main indication for blood transfusions in our study, accounting for 74.23% of cases, including 60.40% of IPH cases. For many authors, obstetric hemorrhages remain the primary reason for transfusions in maternity wards. Chronic iron-folic acid deficiency anemia was also a significant reason for transfusion in our study, accounting for 17% of cases. Louati [11] reports in his study a transfusion for chronic anemia associated with pregnancy in 22.7% of cases, compared to 20.5% found in the study by Ben Ayed et al. [12]. Arezki Bitam [13] reports a prevalence of iron-deficiency anemia during pregnancy of 10% in the 3rd month ; 33.33% in the 6th month ; and 46.66% in the 9th month of pregnancy. The World Health Organization (WHO) [20] estimates that 41.8% of pregnant women (in both developed and developing countries) have anemia. This is a disorder of varying severity affecting 17 to 31% of pregnant women in developed countries and 52.8 to 61.3% in sub-Saharan Africa. This high prevalence of iron deficiency anemia in our study could be linked to undernutrition among our patients, most of whom enter pregnancy already anemic, compounded by the lack of prenatal care (47.30% in our study). This deprives patients of iron and folic acid supplementation, malaria prevention, and intestinal worm prevention. Transfusions in cases of chronic anemia of pregnancy could be prevented by systematic iron supplementation [14, 15]. Malaria, which is endemic in Mali, and sickle cell disease accounted for 4.60% and 4.17% of the reasons for blood transfusions, respectively, in our study. Malaria is a major public health problem in Mali. Preventive opportunities exist only for pregnant women who have been in contact with a health facility. These include the free provision of long-lasting insecticidal nets and the free administration of sulfadoxine-pyrimethamine (SP). Pregnant women who have not received prenatal care do not benefit from these preventive measures. In 99.22% of cases, the blood product administered was whole blood, compared to 0.78% fresh frozen plasma (FFP). Louati [11] reports that 18.18% of transfused patients received fresh frozen plasma (FFP) and were transfused with a combination of at least two types of labile blood products (Red Blood Cells (RBCs) + FFP ± Platelet Concentrates (PCs)) compared to 66.7% in France []. Massive transfusions affected 11.36% of the patients studied, with an average of 5 RBCs transfused per patient [11] , compared to 7.2 RBCs for severe obstetric hemorrhages in Sousse [15]. Louati [11] reports that the average amount of blood transfused in his study was two units of red blood cells (RBCs) per patient in 72.27% of transfused patients. Sherman [16] found that only 0.16% of patients received more than two units of red blood cells (RBCs). We We observed 5 cases of acute pulmonary edema, 4 cases of anaphylactic shock, 3 cases of hyperthermia-chill syndrome, 3 cases of urticaria, and 2 cases of lumbar pain related to blood transfusion. The use of whole blood in almost all cases in our study is due to the fact that it is the most readily available blood product for emergency transfusions. The average quantity of blood products transfused was 1.6 units, compared to an average of 2.45 units requested. This reflects the difficulties in making blood products available in Mali, even in cases of extreme emergency. This situation can further worsen the maternal prognosis. We recorded 18 maternal deaths during this study. These maternal deaths had multifactorial causes, but were largely related to the complete absence, delay, or inadequacy of blood transfusions.
The continuous availability of blood products improves maternal prognosis.
*Correspondence
Ba BERTHE
baberthe61@yahoo.com
Available online : January 22, 2026
1 : Reference health center of Commune V, Bamako, Mali 2 : Mother-Child Hospital Center «Luxembourg» Bamako Mali 3 : Gabriel TOURE University Hospital Center, Bamako, Mali 4 : Faculty of Medicine and Dentistry, 5 : University Hospital Center of Point G, Bamako, Mali © Journal of African Clinical Cases and Reviews 2026
Conflict of interest : None
[1] Kambe KY, Kabran Adjo LC, Koutou N’Guessan C. Les représentations de l’usage clinique des produits sanguins en Côte d’Ivoire : le cas du CHU de Cocody. Rev Ivoir Anthropol Sociol KasaByaKasa. 2018;(38).
[2] Organisation mondiale de la Santé. Transfusion sanguine. Genève : OMS ; 2018.
[3] Mehrabadi A, Liu S, Bartholomew S, Hutcheon JA, Kramer MS, et al. Temporal trends in postpartum hemorrhage and severe postpartum hemorrhage in Canada from 2003 to 2010. J Obstet Gynaecol Can. 2014;36(1):21-33.
[4] Chelli D, Dimassi K, Zouaoui B, Sfar E, Chelli H, et al. Évolution de la mortalité maternelle dans une maternité tunisienne de niveau 3 entre 1998 et 2007. J Gynecol Obstet Biol Reprod. 2009;38:655-61.
[5] Nebout S, Merbai N, Faitot V, Keita H. Prise en charge des hémorragies graves du post-partum. Presse Med. 2014;43(2):111-7.
[6] Khouadja H, Rouissi W, Mahjoub M, Sakhri J, Beletaifa D, Ben Jazia K. Stratégie transfusionnelle des hémorragies graves du postpartum : étude rétrospective à propos de 47 cas. Pan Afr Med J. 2016;25:169. doi:10.11604/ pamj.2016.25.169.7095.
[7] Rahmani A, Belkacem I, Aouissa S, Ouali M. Anémie et grossesse à l’EHS Tlemcen (Algérie). Thèse de doctorat en médecine. Tlemcen ; 2017- 2018. p.7.
[8] Pasquier P, Gayat E, Rackelboom T, La Rosa J, Tashkandi A, Tesniere A, et al. An observational study of the fresh frozen plasma:red blood cell ratio in postpartum hemorrhage. Anesth Analg. 2013;116(1):155-61.
[9] Fouche Y, Sikorski R, Dutton RP. Changing paradigms in surgical resuscitation. Crit Care Med. 2010;38(9 Suppl):S411-20.
[10] Montufar-Rueda C, Rodriguez L, Jarquin JD, Barboza A, Bustillo MC, et al. Severe postpartum hemorrhage from uterine atony: a multicentric study. J Pregnancy. 2013;2013:1-6.
[11] Louati N, Rekik T, Chaabane R, Chaabane K, Mnif H, Gargouri J. Évaluation des pratiques transfusionnelles en milieu obstétrical. J I M Sfax. 2020;(34):15-21.
[12] Ben Ayed B, Chahtour H, Ghorbel B, Mathlouthi N, Trabelsi M, et al. Pratiques transfusionnelles en milieu obstétrical : à propos de 73 cas. J Magh A Réa Méd Urg. 2009;16:15-20.
[13] Khouadja H, Rouissi W, Mahjoub M, Sakhri J, Beletaifa D, et al. Stratégie transfusionnelle des hémorragies graves du post-partum : étude rétrospective à propos de 47 cas. Pan Afr Med J. 2016;25:169-82.
[14] Bitam A, Belkadi N. Prévalence de l’anémie ferriprive au cours de la grossesse dans la wilaya de Blida (Nord de l’Algérie). Nutr Clin Metab. 2008;22(3):100-7. doi:10.1016/j. nupar.2008.07.005.
[15] World Health Organization, Centers for Disease Control and Prevention. Worldwide prevalence of anemia 1993–2005: WHO global database on anemia. Geneva: WHO Press; 2008.
[16] Sherman SJ, Greenspoon JS, Nelson JM, Paul RH. Identifying the obstetric patient at high risk of multiple-unit blood transfusions. J Reprod Med. 1992;37:649-52.
To cite this article :
B Berthe, S Doumbia, H Samake, S Tall, N Sylla, D Goita, SO Traore, OM Traore, I Teguete, I Konate, Y Traore. Study of blood transfusion in patients with an obstetric emergency in three health regions of Mali, case of: Bamako, Ségou, Koulikoro. Jaccr Africa 2026; 10(1): 27-33
